Key Takeaways
- Degenerative disc disease is a common age-related change, not necessarily a progressive disease in the way many patients interpret the word “disease.”
- Degenerative findings are common on MRI even in people without back pain, so the presence of disc degeneration does not automatically identify the source of a patient’s symptoms.
- MRI findings can still be clinically important. Disc herniation, spinal stenosis, nerve compression, fracture, infection, tumor, and other abnormalities may substantially influence diagnosis and treatment when they match the patient’s history and examination.
- The severity of an MRI description does not perfectly predict how much pain or disability someone will experience. Some people with substantial degeneration function extremely well, while others with relatively modest imaging changes can have significant symptoms.
- Treatment decisions should be based on the whole clinical picture: symptoms, neurological findings, physical examination, function, imaging when appropriate, medical history, and response to care.
- Conservative management is appropriate for many mechanical and degenerative spinal conditions, but it is not the correct pathway for everyone. Progressive neurological loss, certain structural conditions, serious pathology, or persistent disabling symptoms may require medication, injections, specialist evaluation, or surgery.
“My MRI Is Terrible.”
Patients sometimes arrive at Doyle Chiropractic carrying an MRI report and say something similar to:
“They told me my back is full of degeneration.”
Or:
“The MRI says degenerative disc disease at four levels. Is my spine wearing out?”
The words on an imaging report can sound alarming.
Terms such as:
- Degeneration
- Disc desiccation
- Disc-space narrowing
- Bulging
- Osteophytes
- Facet arthropathy
can make a patient imagine that the spine is damaged beyond repair.
But an MRI report is a description of anatomy.
It is not, by itself, a complete explanation of why someone hurts.
What Degenerative Disc Disease Actually Means
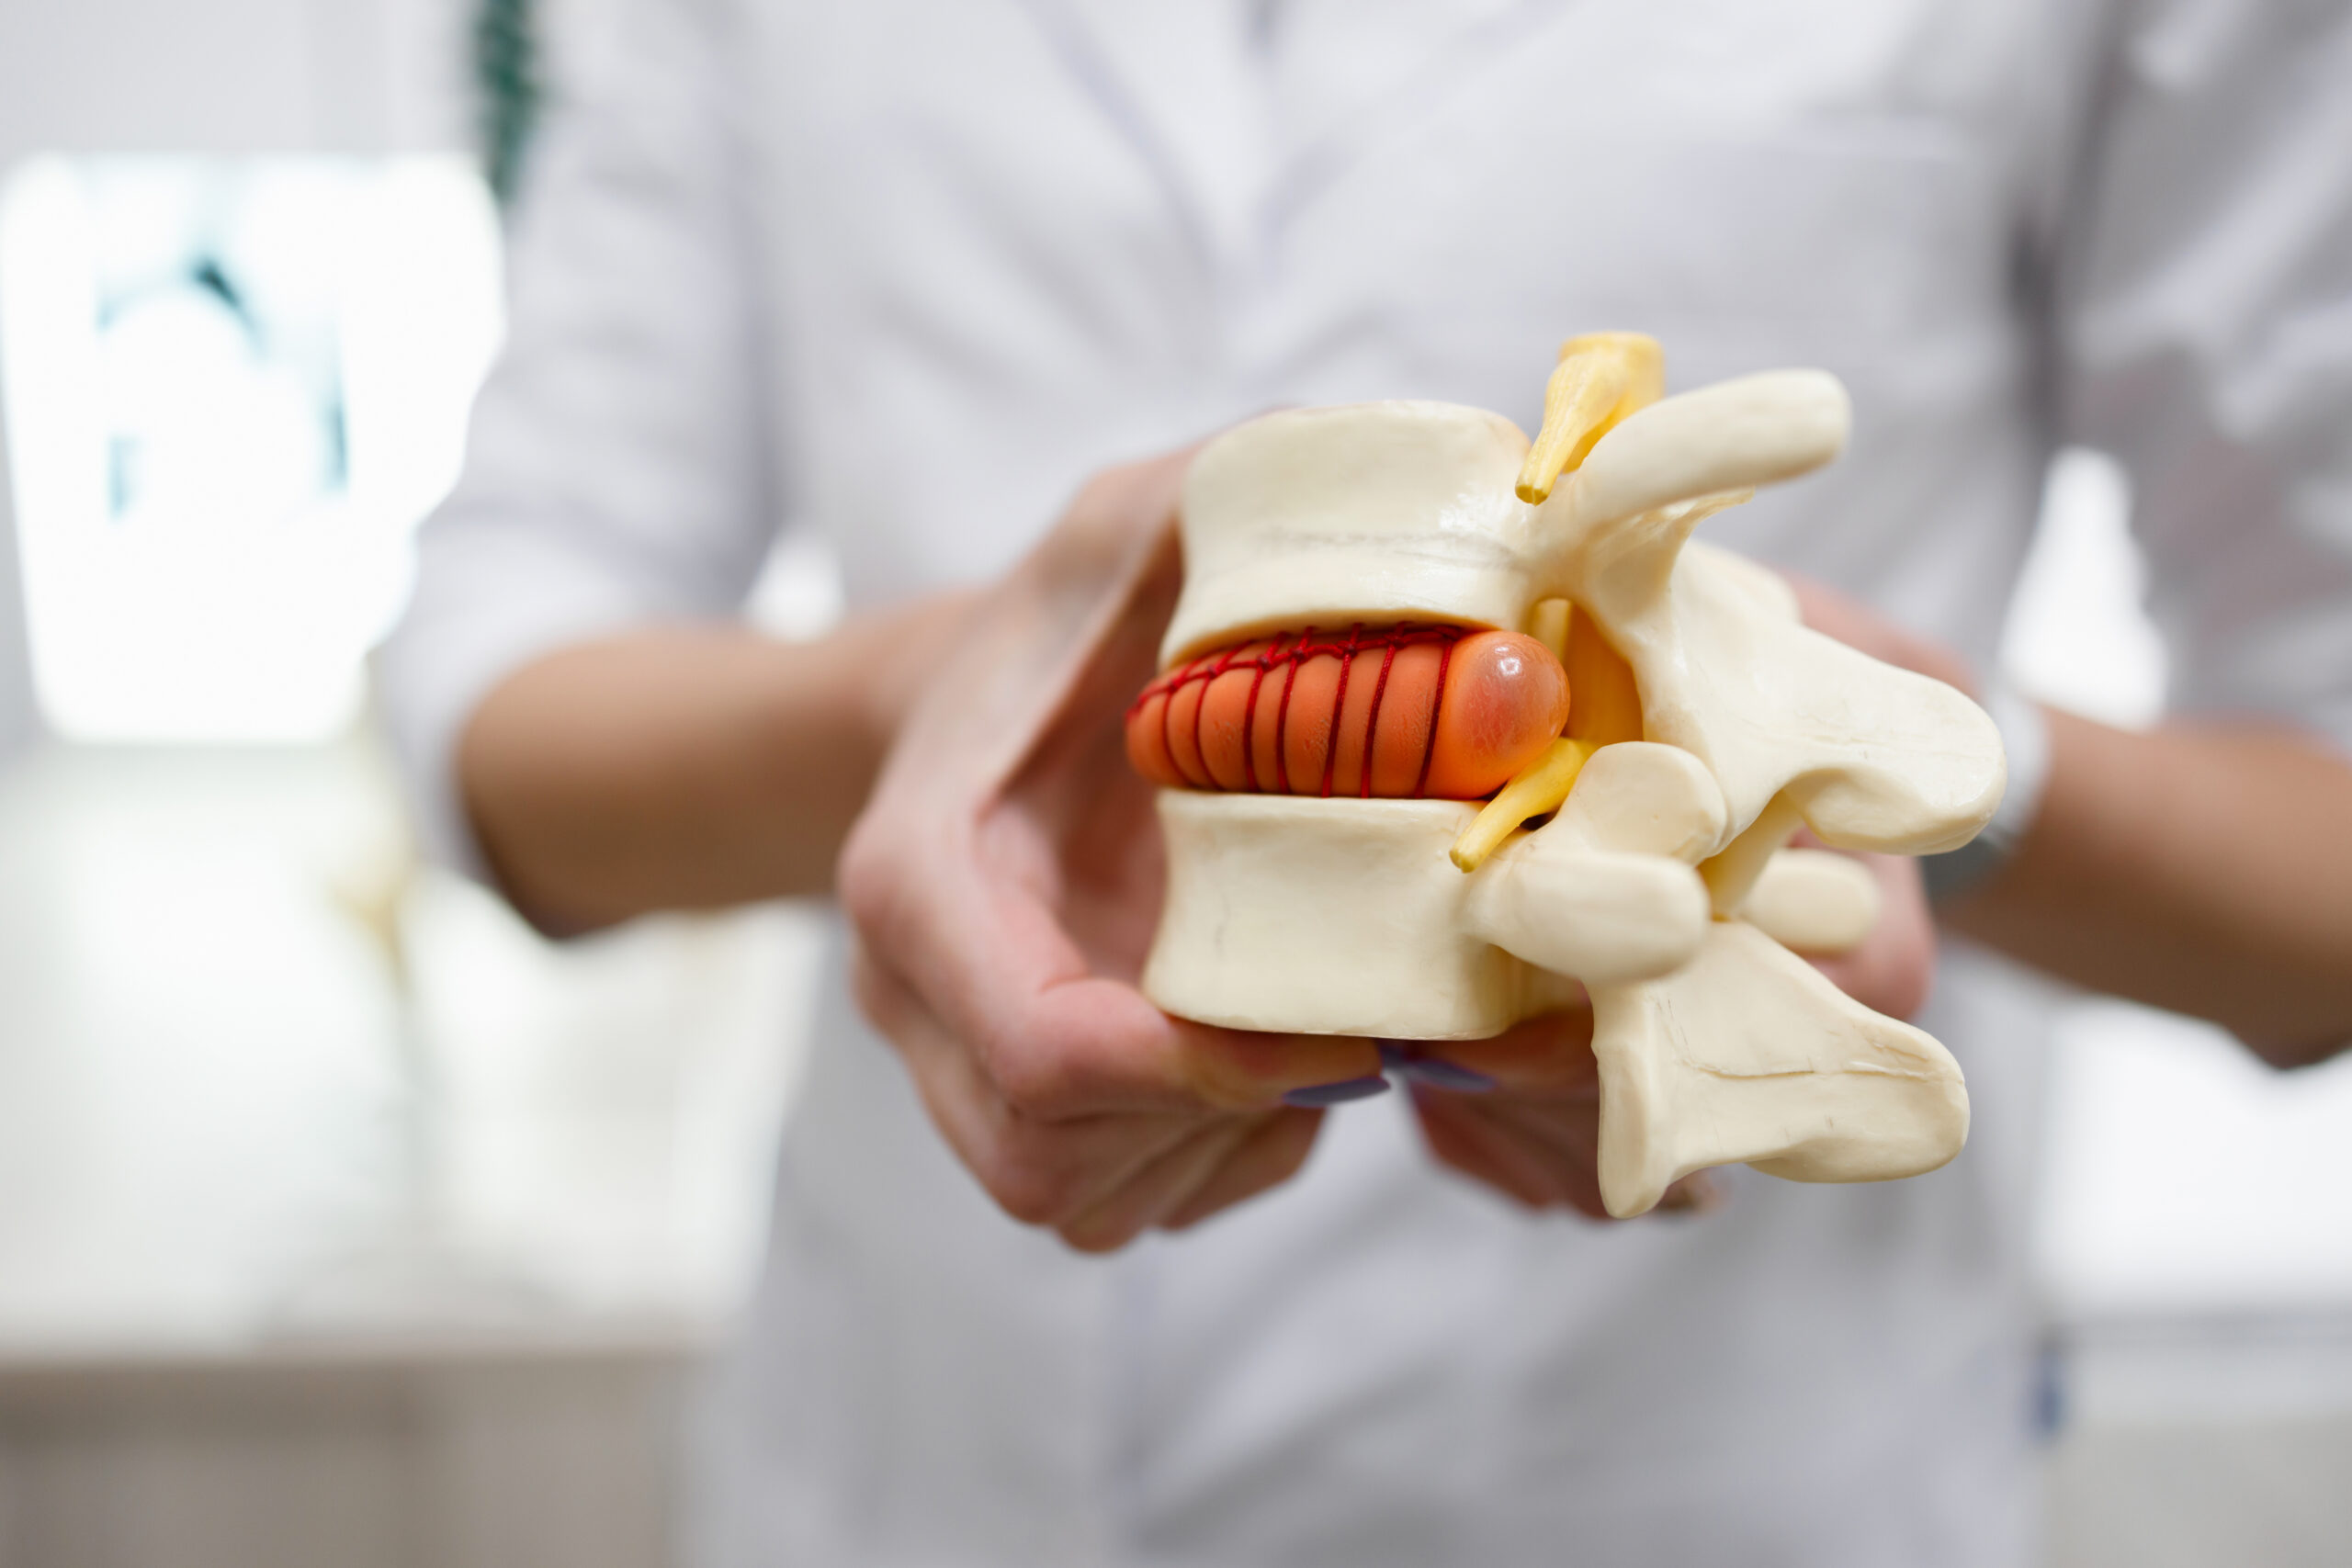
Between most spinal vertebrae are intervertebral discs.
These discs contribute to:
- Load distribution
- Movement
- Spacing between vertebrae
- Overall spinal mechanics
Their structure changes throughout life.
With age, discs commonly lose some water content and undergo changes in their internal composition and shape.
Imaging may describe those changes as:
- Disc desiccation
- Disc degeneration
- Loss of disc height
- Degenerative disc disease
The term degenerative disc disease can be confusing because patients often hear the word disease and assume something abnormal is relentlessly destroying the spine.
In many people, at least some degenerative change is part of normal biological aging.
That does not mean degeneration can never become clinically important.
It means the MRI finding must be interpreted in context.
MRI Can Show Anatomy That Is Not Producing Symptoms
One of the most important concepts in musculoskeletal medicine is that an abnormal-looking image and a painful patient are not necessarily the same thing.
Research examining people without back pain has found that degenerative spinal findings become increasingly common with age.
People who feel perfectly well can have imaging showing:
- Disc degeneration
- Disc bulges
- Disc protrusions
- Facet degeneration
- Other age-related changes
This does not make MRI unreliable.
It means MRI is extremely sensitive at showing anatomy—including anatomy that may not currently be causing symptoms.
Think of MRI as Evidence, Not the Verdict
Imagine a detective investigating a case.
Finding a fingerprint is important.
But the fingerprint has to fit the rest of the evidence.
Spinal imaging works similarly.
If an MRI shows a finding in exactly the right anatomical location and it matches the patient’s:
- Pain distribution
- Neurological findings
- Physical examination
- Symptom behavior
that finding becomes much more meaningful.
If the MRI shows several abnormalities but none corresponds well with the patient’s symptoms, we should be cautious about blaming the scan for everything.
The image contributes evidence.
It does not replace clinical reasoning.
Why MRI Reports Can Sound Worse Than the Patient Feels
Radiologists are responsible for accurately documenting what they see.
That often means an MRI report contains a long list of findings.
A patient may read:
Multilevel degenerative changes.
Disc desiccation.
Facet arthropathy.
Foraminal narrowing.
Disc bulging.
Seeing several findings together can create the impression that the entire spine is failing.
But those words need clinical interpretation.
A radiology report is not designed to tell the patient:
“This finding is definitely causing 73% of your pain.”
That conclusion requires correlation with the patient’s actual presentation.
Degeneration and Pain Are Related—but Not Perfectly
It would also be incorrect to swing too far in the opposite direction and say:
“Degeneration never causes pain.”
Degenerative spinal changes can be clinically relevant.
Depending on the individual, they may contribute to:
- Mechanical back pain
- Reduced spinal mobility
- Facet-joint symptoms
- Foraminal narrowing
- Spinal stenosis
- Nerve-root irritation
- Other structural changes
The important distinction is that the presence of degeneration does not prove that degeneration is the primary pain generator in every patient.
That is why two people with similar MRI reports may function very differently.
A Disc Can Change Without the Spine Becoming “Worn Out”
Patients sometimes visualize degeneration as two bones grinding together because the disc has disappeared.
That is usually an oversimplification.
Degenerative change occurs along a continuum.
A disc may:
- Lose hydration
- Lose some height
- Develop structural changes
while the person remains active and functional.
The surrounding spinal system also includes:
- Vertebrae
- Facet joints
- Ligaments
- Muscles
- Nervous tissue
The body adapts over time.
An aging spine is not automatically a fragile spine.
“Bone on Bone” Is Often More Complicated Than It Sounds
Patients sometimes hear similar language about the spine that they hear about arthritic knees or hips:
“You’re basically bone on bone.”
The phrase may be intended to communicate substantial degenerative narrowing.
But it can create the impression that movement is physically grinding the spine away.
That is not a useful universal interpretation.
Severe degenerative changes can absolutely matter.
But the appropriate treatment decision depends on:
- Symptoms
- Function
- Neurological status
- Structural findings
- Overall health
- Response to conservative treatment
A dramatic phrase should not substitute for those considerations.
The Location of Degeneration Matters
An MRI may describe degeneration at several levels.
For example:
- L3-L4
- L4-L5
- L5-S1
But a patient may have symptoms that point much more strongly toward one level—or toward a problem that is not primarily neurological at all.
If a patient has leg symptoms, we consider whether the anatomical findings correspond with the affected nerve root.
That may involve evaluating:
- Sensation
- Muscle strength
- Reflexes
- Symptom distribution
- Provocative testing
The question is not simply:
“Is there degeneration?”
It is:
“Does this particular finding plausibly explain this particular patient’s symptoms?”
A Disc Bulge Is Not Automatically a Disaster
Disc bulges are common imaging findings.
The term can sound frightening because patients sometimes imagine a disc on the verge of rupturing.
But a bulge can exist without symptoms.
Its significance depends on factors such as:
- Location
- Size
- Relationship to neural structures
- Symptoms
- Neurological findings
A disc finding becomes more clinically compelling when the anatomy and examination tell the same story.
A Herniated Disc Is More Specific—but Still Requires Correlation
Disc herniations can produce nerve-root irritation and radicular symptoms.
A patient may develop:
- Leg pain
- Numbness
- Tingling
- Weakness
depending on the location and severity of the problem.
But even a disc herniation seen on MRI must be correlated with the clinical presentation.
The presence of a herniation does not automatically mean:
- Surgery is necessary
- The patient will have permanent pain
- The disc can never improve
- All future back pain will come from that disc
Many disc-related conditions can improve with conservative management.
Others require more aggressive medical or surgical intervention.
The neurological examination helps determine the difference.
Foraminal Narrowing Matters Most When the Nerve Findings Match
The neural foramina are openings through which spinal nerve roots exit.
Degenerative changes can narrow those spaces.
An MRI may describe:
- Mild foraminal narrowing
- Moderate foraminal narrowing
- Severe foraminal narrowing
Those findings become especially important when the patient has corresponding:
- Radiating pain
- Numbness
- Tingling
- Weakness
- Reflex changes
But severe-sounding imaging terminology without corresponding clinical findings should still be interpreted thoughtfully.
We treat patients, not adjectives on MRI reports.
Spinal Stenosis Is More Than Just “Arthritis in the Back”
Lumbar spinal stenosis involves narrowing that can affect neural structures.
Some patients develop a characteristic pattern of:
- Leg aching
- Heaviness
- Numbness
- Weakness
- Reduced walking or standing tolerance
Symptoms may improve with sitting or bending forward.
That clinical pattern provides information that the MRI alone cannot.
A patient with significant radiographic stenosis who walks comfortably for miles is clinically different from someone whose leg symptoms force them to sit after several minutes of standing.
Function matters.
Facet Arthritis Can Also Appear on MRI
The facet joints are small joints at the back of the spine.
Like other joints, they can develop degenerative changes.
Imaging may use terms such as:
- Facet arthropathy
- Facet hypertrophy
- Facet degeneration
These findings can contribute to certain mechanical pain presentations.
But again, seeing facet arthritis does not prove that every episode of back pain originates from those joints.
The patient’s movement pattern and examination remain important.
Why Your Pain Can Change Even When Your MRI Does Not
This is one of the most useful concepts for patients to understand.
An MRI may look essentially the same while the patient goes from:
- Severe pain
to:
- Mild pain
to:
- No pain
and sometimes back again.
Why?
Because pain is influenced by more than static anatomy.
Factors can include:
- Tissue irritation
- Recent workload
- Strength and conditioning
- Sleep
- Recovery
- Movement tolerance
- Neurological sensitivity
- Overall health
- Other biological and psychosocial influences
The MRI is a snapshot of structure.
The patient is a changing biological system.
This Is Why a Five-Year-Old MRI May Not Explain Today’s Episode
Suppose an MRI performed five years ago showed degeneration at L4-L5 and L5-S1.
The patient improved and lived normally for years.
Then back pain returns after an unusually demanding week.
It would be easy to say:
“Those discs are acting up again.”
Maybe.
But that conclusion should not be automatic.
The current episode still deserves a current clinical assessment.
Old imaging provides history.
It does not eliminate the need to understand what is happening now.
More Degeneration Does Not Automatically Mean More Pain
Patients sometimes assume that if one MRI showed degeneration and a later MRI shows progression, pain must inevitably worsen.
The relationship is not that simple.
Structural aging can continue while symptoms:
- Improve
- Remain stable
- Fluctuate
- Disappear
This is one reason treatment goals should include function rather than attempting to make an aging MRI look young again.
We cannot promise to reverse ordinary structural aging.
We can often work on how well the person moves and functions despite those changes.
MRI Findings Should Not Make Patients Afraid to Move
One potential problem with imaging is not the technology itself.
It is how the findings are interpreted.
If a patient believes:
“My discs are deteriorating, so every time I bend I’m damaging them more.”
they may begin avoiding normal activity.
For many mechanical and degenerative spinal conditions, appropriate movement and exercise are beneficial rather than destructive.
Restrictions may be appropriate for certain injuries or conditions.
But permanent fear of normal movement should not be the default response to age-related degeneration.
Conservative Care Does Not Mean Pretending the MRI Is Normal
A balanced approach is not:
“Ignore your MRI.”
It is:
“Understand what the MRI shows, determine which findings actually matter clinically, and choose treatment accordingly.”
For some patients, conservative management may reasonably include:
- Therapeutic exercise
- Progressive strengthening
- Activity modification
- Chiropractic or manual treatment when appropriate
- Education
- Other condition-specific conservative therapies
For another patient, the MRI and neurological examination may indicate that medical or surgical consultation deserves greater priority.
Both can be appropriate decisions.
Medication Can Be an Appropriate Part of Management
Patients sometimes arrive believing they must choose between:
“Medication or natural treatment.”
That is often an unnecessary either-or choice.
Depending on the diagnosis and patient’s medical history, medications may have an appropriate role in controlling:
- Pain
- Inflammation
- Neuropathic symptoms
- Muscle spasm
- Other associated problems
Medication decisions belong with the appropriate prescribing clinician.
Conservative musculoskeletal treatment can sometimes occur alongside medical management.
The objective should be coordinated care—not competition between professions.
Injections May Be Appropriate for Selected Patients
Spinal injections are not necessary for every patient with degeneration.
But selected patients may benefit from interventional procedures depending on:
- Diagnosis
- Symptom severity
- Neurological involvement
- Response to conservative treatment
- Functional limitation
An injection and rehabilitation are not necessarily mutually exclusive.
In some cases, reducing symptoms can help a patient participate more effectively in rehabilitation.
The decision should be individualized.
And Sometimes Surgery Really Is the Right Recommendation
A responsible conservative-care discussion must acknowledge this clearly.
Surgery may be appropriate when a patient’s condition involves circumstances such as:
- Progressive neurological loss
- Certain severe nerve-compression syndromes
- Structural instability
- Severe persistent symptoms despite appropriate nonsurgical management
- Other surgically remediable pathology
The decision depends on the diagnosis and the patient’s complete clinical picture.
The goal of conservative care should never be to prevent a patient from receiving surgery they genuinely need.
It should be to determine when a reasonable nonsurgical pathway exists—and when it does not.
The Most Important Question Is Not “How Bad Is My MRI?”
A more useful series of questions is:
What symptoms do I have?
What does the examination show?
Do the MRI findings match those symptoms and findings?
How much is the problem limiting my life?
Are there neurological deficits or other concerning features?
What treatment options are reasonable before considering more invasive care?
And is there anything about my presentation that makes specialist or surgical evaluation more appropriate now?
That is how an MRI becomes clinically useful.
It becomes one important piece of a much larger picture.
How Doyle Chiropractic Evaluates a Patient With Degenerative Findings on MRI
When a patient brings an MRI to Doyle Chiropractic, the goal is not simply to count how many abnormal findings appear in the report.
Dr. Geoffrey Doyle considers whether those findings make sense in the context of the patient’s current problem.
That begins with the history.
Important questions may include:
- Where is the pain?
- Does it remain in the back or travel into the leg?
- Is there numbness or tingling?
- Has strength changed?
- How long can the patient comfortably sit, stand, or walk?
- Which movements improve or aggravate symptoms?
- Was there a recent injury?
- Has the patient had similar episodes before?
- Are symptoms improving, worsening, or remaining unchanged?
The MRI becomes considerably more useful once those answers are known.
The Neurological Examination Can Be More Important Than a Dramatic MRI Description
When symptoms suggest possible nerve involvement, the examination may include assessment of:
- Muscle strength
- Sensation
- Reflexes
- Nerve-tension findings
- Walking and balance when relevant
- Other neurological functions based on the presentation
Suppose an MRI describes foraminal narrowing at a particular lumbar level.
If the patient also demonstrates pain, sensory changes, weakness, or reflex findings corresponding with the affected nerve root, the imaging finding becomes more clinically compelling.
Conversely, an impressive-looking MRI finding with no corresponding symptoms or examination findings may be less important to the current complaint.
This process is called clinical correlation.
It is one of the most important principles in interpreting musculoskeletal imaging.
The Examination Also Looks at What the Spine Can Still Do
Imaging tells us about structure.
Physical examination tells us about function.
Depending on the presentation, we may evaluate:
- Spinal movement
- Hip function
- Strength
- Movement tolerance
- Repeated movement response
- Functional tasks
- Walking or standing tolerance
A patient may have substantial degenerative findings yet demonstrate excellent strength and function.
Another patient may have relatively modest imaging changes but considerable functional limitation.
Both deserve an individualized plan.
Treatment Should Target the Patient, Not an MRI Finding
There is no single “degenerative disc disease treatment.”
Management depends on what the degeneration is actually associated with.
A patient with uncomplicated mechanical low-back pain may require a different plan from someone with:
- Lumbar radiculopathy
- Spinal stenosis
- Significant facet-related symptoms
- Severe neurological compromise
- Another structural condition
For appropriately selected patients, conservative care may include:
- Therapeutic exercise
- Progressive strengthening
- Mobility work
- Activity modification
- Chiropractic or manual treatment
- Education about movement and recovery
- Other diagnosis-specific interventions
The treatment plan should address the patient’s functional problem rather than attempting to make the MRI appear younger.
Exercise Does Not “Wear Out” a Degenerative Spine
One of the most damaging conclusions a patient can draw from an MRI is:
“I shouldn’t exercise because my discs are already worn down.”
For many people with degenerative spinal conditions, appropriately selected exercise is an important component of management.
Depending on the patient, rehabilitation may work on:
- Trunk strength
- Hip strength
- General conditioning
- Walking tolerance
- Mobility
- Lifting capacity
- Balance
- Return to recreational activity
Exercise should be adjusted when necessary for the diagnosis and symptom severity.
But an MRI showing degeneration does not automatically mean the spine should be protected from normal loading indefinitely.
Chiropractic and Manual Treatment
Chiropractic or other manual treatment may be appropriate for selected patients with mechanical symptoms associated with degenerative spinal conditions.
Potential goals may include improving:
- Comfortable movement
- Short-term symptom control
- Functional tolerance
- Ability to participate in rehabilitation
Manual treatment does not:
- Reverse normal spinal aging
- Rehydrate a severely degenerated disc back to its youthful state
- Remove arthritis
- Guarantee that a disc bulge disappears
- Replace necessary neurological or surgical evaluation
It should be used when clinically appropriate as part of a broader management strategy.
Spinal Decompression Requires Diagnosis-Specific Expectations
Nonsurgical spinal decompression may be considered in selected patients depending on the clinical diagnosis and presentation.
It should not be offered simply because an MRI contains the words:
“Degenerative disc disease.”
The presence of degeneration alone does not tell us whether decompression is appropriate.
When used, expectations should remain realistic.
Nonsurgical decompression should not be presented as a way to permanently reverse all degenerative changes seen on MRI.
The relevant question is whether a particular patient and condition are reasonable candidates for that form of conservative care.
Class IV Laser Therapy
Class IV laser therapy may also be incorporated as an adjunct for selected musculoskeletal conditions when clinically appropriate.
Its role should be based on the condition being treated rather than on the existence of an abnormal MRI.
Laser therapy does not:
- Rebuild a severely degenerated disc
- Reverse advanced spinal arthritis
- Eliminate structural stenosis
- Correct progressive neurological loss
- Replace surgery when surgery is indicated
It may be one component of conservative management for appropriately selected conditions, but it should not be described as an anatomical reversal of spinal aging.
The Dr. Doyle Perspective
“I see patients who hand me an MRI and say, ‘Doc, my back is a mess.’ Sometimes they’ve been carrying that idea around for years. I want to look at the MRI, but then I want to look at the patient. Can they walk? Can they bend? Are they strong? Are there neurological changes? Does the level that looks bad on the MRI actually match where their symptoms go? I’ve seen people with significant degeneration who function extremely well, and I’ve seen people with a relatively ordinary-looking MRI who are really hurting. The picture matters, but it doesn’t get to tell the whole story. Our job is to connect the imaging to the person standing in front of us.”
— Dr. Geoffrey Doyle, DC
Our Clinical Experience
Consider several patients who all have an MRI report containing the phrase degenerative disc disease.
One patient has localized low-back pain after an increase in lifting and yard work. The neurological examination is normal, walking is comfortable, and symptoms behave mechanically. The degenerative findings may provide background information, but the patient’s current presentation may still be managed conservatively.
Another patient has low-back pain accompanied by pain traveling down the leg, numbness, and measurable weakness. If the MRI shows pathology corresponding to that nerve distribution, those imaging findings become considerably more important.
A third patient has multilevel lumbar stenosis and finds that standing or walking progressively produces leg heaviness and discomfort, while sitting provides relief. That clinical pattern may correlate much more closely with the imaging.
A fourth patient has severe back pain but an MRI containing only relatively modest age-related changes. That does not mean the patient’s pain is imaginary or insignificant. It means pain intensity cannot simply be calculated from the number of degenerative findings on a scan.
And another patient may have progressive neurological deficits or another finding that makes specialist evaluation more appropriate than continuing routine conservative treatment.
The words on the MRI may be similar.
The patients are not.
A Second Opinion Does Not Have to Mean Rejecting the First Opinion
Patients sometimes seek conservative care after being told they may eventually need:
- Medication
- An injection
- Surgery
Seeking another opinion does not require assuming the first clinician was wrong.
Sometimes another evaluation confirms that surgery is appropriate.
Sometimes it identifies a reasonable period of conservative management first.
Sometimes treatment involves both conservative and medical care.
Good healthcare should allow those possibilities.
The question is not:
“Which profession is right?”
It is:
“Which treatment pathway best fits this patient right now?”
When Medication May Be Reasonable
Medication can play an appropriate role in spinal care.
Depending on the condition, a prescribing clinician may consider medications for:
- Acute pain
- Inflammatory symptoms
- Neuropathic pain
- Muscle spasm
- Other relevant symptoms
Medication may sometimes make it easier for a patient to:
- Sleep
- Move
- Participate in rehabilitation
- Function during an acute episode
Medication does not have to represent treatment failure.
Likewise, a patient who prefers to minimize medication should still make those decisions with the appropriate healthcare professional rather than abruptly changing prescribed treatment.
When an Injection May Be Reasonable
Injections may be considered for selected spinal conditions when the diagnosis and symptom pattern support their use.
Depending on the situation, they may be used to:
- Reduce symptoms
- Address particular pain generators
- Help manage radicular symptoms
- Facilitate function or rehabilitation
Their benefits and limitations depend on the procedure and diagnosis.
A patient can receive an injection and still participate in conservative rehabilitation.
These approaches are not necessarily competitors.
When a Surgical Consultation Becomes More Important
There are circumstances in which delaying appropriate specialist evaluation is not a virtue.
Surgical or neurological consultation may become particularly important with findings such as:
- Progressive motor weakness
- Significant or worsening neurological deficits
- Certain severe compressive conditions
- Structural instability
- Persistent disabling symptoms despite appropriate conservative management
- Other pathology for which surgery may offer meaningful benefit
Emergency evaluation is necessary when symptoms suggest conditions such as cauda equina syndrome, including new bowel or bladder dysfunction associated with neurological symptoms, saddle-region sensory loss, or other severe neurological changes.
Conservative care should have clear boundaries.
Surgery Is Not a Failure of Conservative Care
This distinction matters.
If a patient receives appropriate conservative management but continues to experience severe functional limitation from a surgically remediable condition, moving to surgery does not mean the previous care failed.
It may mean the patient followed a reasonable stepped-care pathway and has reached the point where another treatment offers greater potential benefit.
Likewise, avoiding surgery when a patient can recover satisfactorily without it is also reasonable.
The objective is not to prove that one treatment philosophy always wins.
It is to help the patient make an informed decision.
Sometimes the Best Outcome Is Better Function, Not a Better MRI
Patients occasionally expect treatment to produce a follow-up MRI showing that degeneration has disappeared.
That is usually not a realistic goal.
A more meaningful outcome may be that the patient can once again:
- Walk comfortably
- Work
- Exercise
- Sleep
- Travel
- Lift
- Play golf
- Care for children or grandchildren
- Perform ordinary daily activities
while the underlying age-related imaging findings remain.
That distinction can fundamentally change how someone thinks about recovery.
An MRI Should Inform Your Future—Not Define It
There is a major difference between telling a patient:
“You have degeneration.”
and telling them:
“Your MRI shows degenerative changes. Now let’s determine which findings matter, what your examination tells us, what you can safely work on, and what treatment options make sense.”
The first statement can leave someone feeling damaged.
The second creates a clinical plan.
Frequently Asked Questions
Is degenerative disc disease really a disease?
The terminology can be misleading. Degenerative disc disease generally describes age- and load-related structural changes in spinal discs. It can be associated with symptoms, but degenerative findings are also common in people without pain.
Does degeneration on MRI mean that is what is causing my back pain?
Not necessarily. Degenerative findings become increasingly common with age and can exist without symptoms. The MRI needs to be correlated with your history, examination, neurological findings, and symptom pattern.
Can severe degeneration exist without severe pain?
Yes. Imaging severity and pain severity do not have a perfect relationship. Some people with substantial degenerative findings function very well.
Does a disc bulge mean I have a serious back problem?
Not automatically. Disc bulges are common and can be asymptomatic. Their importance depends on location, symptoms, neurological findings, and whether the imaging corresponds with the clinical presentation.
Can degeneration cause a pinched nerve?
Degenerative changes can contribute to narrowing around spinal nerve roots and may produce radicular symptoms in some patients. Symptoms and neurological examination help determine whether a nerve is clinically affected.
Can degenerative disc disease be reversed?
Normal age-related structural changes generally should not be approached with the expectation that treatment will restore the spine to its youthful appearance. Treatment often focuses instead on reducing symptoms and improving strength, movement, function, and activity tolerance.
Will exercise make degeneration worse?
For many patients, appropriately selected exercise is beneficial and is an important component of conservative management. Exercise should be individualized when significant neurological, structural, or medical issues are present.
Should I avoid bending because my discs are degenerating?
Not simply because an MRI shows degeneration. Normal spinal movement is not automatically harmful. Certain conditions may require temporary modification, but permanent avoidance of ordinary movement is usually not the default goal.
Do I need another MRI every time my back hurts?
Usually not. Repeat imaging is most useful when there has been a meaningful clinical change, concerning neurological or medical findings, significant trauma, or another reason the new imaging would affect management.
Can chiropractic care help if I have degenerative disc disease?
Some patients with mechanical symptoms associated with degenerative spinal conditions may benefit from conservative care that includes exercise, activity guidance, and appropriate manual treatment. The suitability of chiropractic care depends on the diagnosis, neurological findings, structural considerations, and overall health.
If a surgeon recommends surgery, should I always try chiropractic treatment first?
No. Some conditions require timely surgical evaluation, and delaying appropriate care can be harmful. In other situations, a trial of conservative management may be reasonable. The correct sequence depends on the diagnosis and severity of the condition.
Can I use medication and receive conservative care at the same time?
Often, yes. Medication prescribed by the appropriate healthcare professional and conservative musculoskeletal care can be complementary when both are clinically appropriate.
Does needing an injection mean conservative care failed?
No. An injection may be one component of a broader treatment plan and can sometimes be used alongside rehabilitation.
What symptoms make nerve compression more concerning?
Progressive weakness, worsening neurological loss, significant gait changes, or severe neurological symptoms deserve prompt assessment. New bowel or bladder dysfunction associated with neurological symptoms or saddle-region sensory loss requires emergency evaluation.
What should I focus on instead of the words in my MRI report?
Focus on the relationship between:
- Your symptoms
- Your examination
- Your neurological status
- Your function
- Your imaging
- Your response to treatment
That combination provides a much more useful picture than any single MRI phrase.